2026 Health Plan Funding Simulator Methodology
How the 2026 edition of the Benefitra Funding Simulator works, and what it can't tell you
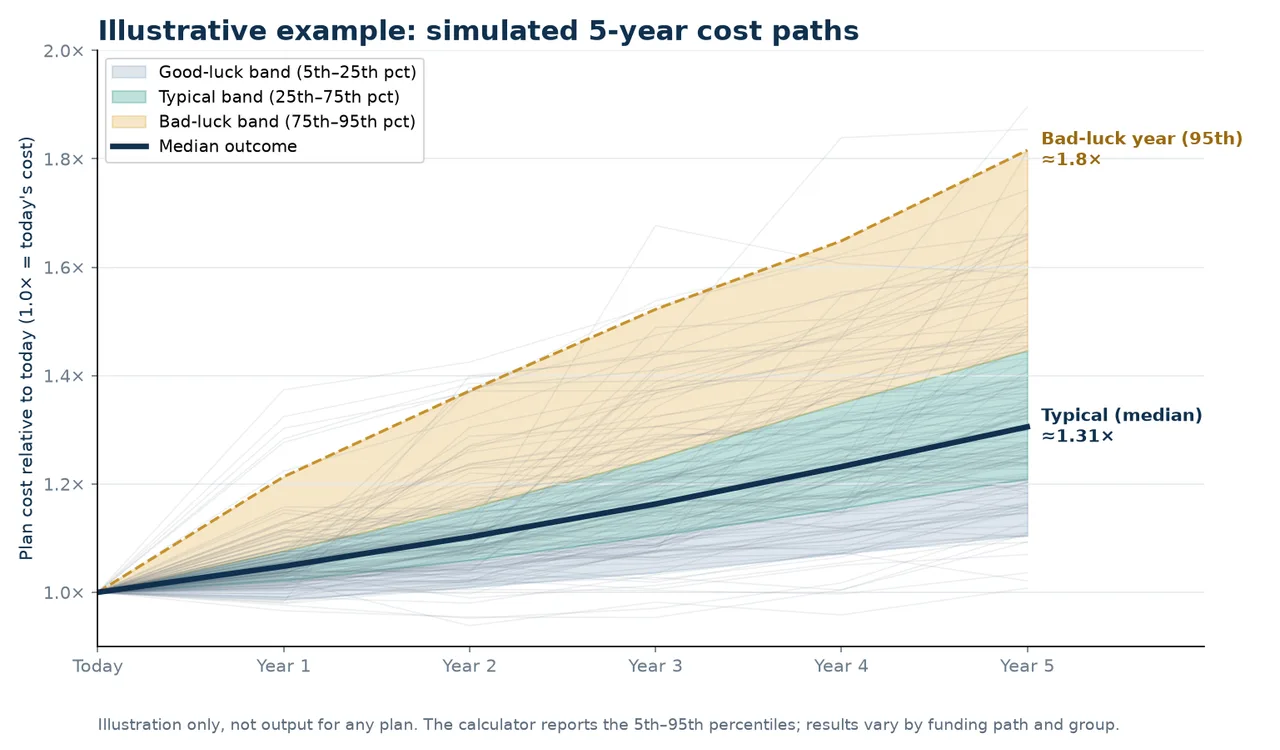
This is a plain English, deliberately honest account of Benefitra's 2026 health plan funding simulator methodology. At the heart of this simulator is a Monte Carlo simulation model. It runs your group's next five years thousands of times. For each member, the likelihood of catastrophic conditions is adjusted based on age and health. Each funding path is then priced using its own real world rating rules, which means that instead of one single forecast you get a realistic range of likely costs.
This page is for employers who are considering renewals or new funding options. It serves brokers and advisors too as they support these decisions. Also included are decision makers from small to mid sized companies (with roughly 5 to 500+ employees). We explain how the model compares fully insured, level funded, self funded, captive, PEO, Taft-Hartley, MEWA and ICHRA plans. We describe what inputs are used, how cost containment overlays impact results, how to interpret scenario ranges and volatility, and we also discuss both where the model has been tested and where it falls short.
Why should you care? Choosing how to fund a group health plan is a risk decision as much as a pricing one. It involves weighing not just lower expected costs versus higher expected costs but also comparing predictable premiums with exposure to claim volatility. You can use the simulator to pressure test quotes and renewals against modeled five year outcomes. This allows you to make a more informed decision that takes the risk into account.
1. What the tool does and who it's for
Choosing how to fund a group health plan is one of the highest stakes decisions a small or mid sized employer makes all year. The same benefits can be delivered through quite different financial arrangements. Each option has its own mix of characteristics, which are how predictable the cost is, how much you gain in a good claims year, and how exposed you are when things go wrong.
The Benefitra Funding Simulator aims to make this trade off clear. You describe your group, such as its size, state, ages of members and what you pay currently. Then the tool estimates what each funding path is likely to cost over a five year horizon, including the unlucky years, and not just next year. It’s really focused on showing renewal trajectories. While you have a rough idea of payments today, what you cannot see clearly is how each funding type's cost changes over those five renewals or how much the path fluctuates.
Who it's for and the benefits
| WHO | HOW THEY USE IT |
|---|---|
| Small and midsized businesses (roughly 5 to 500+ employees) | Weighing whether to stay fully insured or move toward level funded, self funded, captive, or pooled arrangements |
| Brokers and advisors | A transparent, sharable way to frame the funding conversation with a client, improving understanding of the trade off between protection and control |
| Anyone weighing a quote or renewal | Pressure testing a carrier quote or a renewal against a modeled range before signing |
The health plans and funding arrangements it compares
We run seven different funding arrangements through the full Monte Carlo simulation. We add an eighth as well, a deterministic Comparable ICHRA benchmark that can be added via a button. Each of the seven arrangements stands alone, with its own rating rule, and they act differently in terms of renewals. The tool never merges two of these arrangements together. This collection consists of Fully Insured, PEO, Taft-Hartley, MEWA, Level Funded, Self Funded, Self Funded Captive, and finally ICHRA which you can add via the button.
None of these is a relabeled version of another. Each one renews on its own rules.
Level Funded and Self Funded are both ways to self fund, but there are differences. Level Funded is self funding inside a carrier package that includes bundled stop loss insurance and a TPA, fixed monthly payments that give you predictable monthly expenses, and part of a good year’s surplus refunded. It carries its own aggregate corridor billed monthly. Self Funded on the other hand is traditional self funding, where the group funds claims directly. The two price and renew differently, and Section 3 details how. Unbundled self funded arrangements can also let an employer opt for top tier providers rather than taking a single carrier package.
Taft-Hartley and MEWA are two different pooled trust presentations. Under the Taft-Hartley pooled trust, everyone gets the same pooled result, a renewal on a bounded distribution around a selected average renewal. A MEWA can be experience rated on each group’s own claims, and so they do not renew in the same way.
The eighth option stands apart. There is a button that allows you to add it (a Comparable ICHRA employer cost overlay, which is a deterministic benchmark relative to the individual market premium and not a full simulation). That way, you can size an ICHRA against the other seven modeled arrangements.
State laws take precedence. If a state's statutes restrict small group stop loss coverage (and so self funding), then this tool simply removes those paths from your comparison automatically. It doesn't list them in any way suggesting they are available to buy. The self funded captive is also withheld for the very smallest groups, the ones that fall below the enrollment floor set by the program.
Want more? We've written about how different funding types vary and which suits your risk, and about stop loss and self funding regulations by state.
2. How the model works
At its core, this is a Monte Carlo simulation. Modeling steps are performed in sequence to turn your inputs into five year financial projections. Rather than assume a single “expected” claims year and then multiply it out, this simulation plays your group’s next five years forward thousands of times. A different plausible claims experience is drawn every time. By default, there are 5,000 simulated futures for groups with 50 or fewer enrolled employees and 2,000 for larger ones. This disparity is because small groups have the lumpiest tails, and you need the most runs to resolve that. You can choose anywhere from 500 to 10,000 simulation runs. The spread of results across those runs is the answer (a single number estimate throws that spread away).
The condition incidence catastrophe engine
The most critical thing to understand about this model is where the risk really comes from. Older calculators rely on just one blended “catastrophe” number and they stretch that number using a volatility knob. We simulate the actual events directly instead. Every year for each member, we draw 17 named catastrophic conditions (solid cancer, blood cancer, kidney failure on dialysis (ESRD), organ transplant, heart attack, coronary bypass surgery, chronic congestive heart failure, NICU / premature birth, hemophilia, multiple sclerosis, autoimmune disease treated with biologics, cystic fibrosis, one time gene therapy, joint replacement, complex spine surgery, stroke, and severe sepsis), plus a catch all “other catastrophic” bucket for high cost events outside that list. So there are 18 condition types in all and we sample each at the member's incidence rate based on age and health.
The draw is a Poisson process over each member’s per year probability. This means a 30 life group either has a catastrophic case this year or it doesn’t, and there is no smooth average that can hide the lumpiness. When a condition fires, its cost is sampled from a right skewed distribution (most cancers are expensive, a few are catastrophic), and the case is carried forward with multiyear persistence. So a year 1 dialysis, cancer, or transplant loads years 2 through 5 in the same way it would in a real book. The heavy upper tail is not dialed in by hand. Instead it comes out of the arithmetic, because small pools are lumpy and dangerous while large pools smooth out. (The main cost charts report that tail out to the 95th percentile. The cost containment chart also shows the 99th percentile so you are able to see how containment acts on the most extreme simulated years. You should treat that edge as a rough read, because it rests on few simulation runs.)
The three component claims model
Underneath, the claims for each simulated year are the sum of three parts, and each part behaves in a different way.
- A deterministic baseline. This is the floor of routine, always present spend, and it keeps even a good year from dropping to zero.
- A chronic / routine component. This is moderate, correlated year to year variation that comes from the ordinary ebb and flow of a covered population’s health. It is modeled with memory, so a bad chronic year tends to be followed by another one.
- A catastrophe component. This is the heavy tailed part, and it is now fully produced by the condition incidence engine described above. It carries most of the year to year variance, and it is what the adverse year and catastrophic year outputs are truly measuring.
On average, the three components sum up to the group's expected claims. The design allows us to identify which component drives volatility and to calculate the average claims level separately from the tail risk. We deliberately separated them that way because high cost claims research, including Sun Life’s High Cost Claims and Injectable Drug Trends reports (listed in the References), shows that a small share of members accounts for a large share of healthcare spending overall. So the bulk of risk when it comes to health plan funding lies in that tail.
An honest word on what the condition engine moves and what it doesn't. Because the model pins each run’s average catastrophe cost to the group’s expected budget, details about individual conditions don’t really swing the headline (typical year) number very much. What do they affect? They change the shape of the bad year tail (the upper 75th to 95th percentile outcomes). And they also change the read on whether your group is healthier or sicker than the community pool. It’s right there that the funding decision is actually won or lost. We made this modeling trade off deliberately, and we are calling it out so you know what the engine is precise about and what it isn't.
The 5 year risk adjusted recommendation
The tool’s “most likely to perform well over five years” pick is explicitly risk adjusted. It is meant to help decision makers evaluate options rather than just pick the path with the lowest average cost. Each eligible path is scored on its expected five year cost and penalized by its downside (how much worse a bad luck run comes out than expected at your group’s size). It is also aligned with the structural signal from Section 3 (whether your own risk sits above or below the community pool). In plain terms, it favors the path that pairs a low expected cost with a tight, contained downside, and not the one that only looks lowest cost in an average year while hiding a fat tail. A healthy 300 life group scores strongly toward self funding. A healthy 15 life group scores toward level funded (where stop loss caps the volatility). A sicker small group scores toward the shelter of community rated fully insured, which can lead an employer toward more protection or more control depending on the risk picture.
3. Community rating and funding type pricing
Let's read this part carefully. This is what makes the tool stand out from a generic cost calculator. The same simulated claims experience produces very different employer healthcare costs depending on the way you fund the plan. Each path responds to your group's own health through an entirely different mechanism. Blending them all into one cost model for pricing would be wrong from an actuarial point of view. So the tool prices each path using its real rating rule.
| FUNDING TYPE | RATING REGIME | DOES YOUR OWN HEALTH MOVE THE PRICE? |
|---|---|---|
| Small group Fully Insured | ACA community rating | No. Federal rules allow only age (3:1), area, tobacco (up to 1.5:1) and family tier. New York and Vermont allow no age rating |
| Large group Fully Insured | Experience rating (credibility weighted) | Yes, blended with the manual rate at your credibility |
| PEO | The PEO's own rating curves. Reunderwritten on your claims | This plan provides the Massachusetts tax document showing that you have health insurance. Renewals are modeled around a default of about 13% a year (a Benefitra modeling assumption, not a published national average), with occasional much larger jumps |
| Taft-Hartley (pooled trust) | Community/pooled. One renewal for everyone | No, pooled. The 2026 edition centers the shared renewal at about 3% a year (Benefitra modeling assumption) |
| MEWA | Pooled trust, but can be experience rated | Sometimes. An experience rated MEWA rerates on your own claims, so it does not renew like Taft-Hartley |
| Level Funded | Self funding in a carrier package, medically underwritten at setup. Own aggregate corridor billed monthly | This plan provides the Massachusetts tax document showing that you have health insurance. Underwriting is why healthy groups get submarket offers. Renews on the package's own basis |
| Self Funded | Traditional self funding. Funds claims directly + stop loss | Yes, fully. Driven by your own incidence and persistence. Renews on its own basis (not the level funded corridor) |
| Self Funded Captive | Self funding + a shared risk captive layer | Yes, fully. Own claims, with a partly refundable pooled layer |
Community rated fully insured is blind to your group's health
In most states a small group is 1 to 50 employees. In California, New York and Vermont it's 1 to 100. Inside that range fully insured premiums are community rated, and your group’s claims don’t touch your price. Under the ACA’s adjusted community rating, a small group fully insured premium may vary only by age (capped at 3:1 across adults), geographic area, tobacco use (up to 1.5:1), and family tier. New York and Vermont go further. They don’t allow price differences by age at all, so the simulator applies no age rating in those two states. Why do employers like this structure? Monthly expenses are predictable. Control and transparency are more limited, though.
For the renewal, the 2026 edition starts from your state’s six year average of filed small group rate changes for plan years 2021 to 2026 (CMS Unified Rate Review public use files3). That average is used for every year of the five year path. You can overwrite it with your own expectation or with your carrier’s renewal. What your members actually cost won't move it. Yes, the condition incidence engine still runs for a community rated group in the model. But it only computes your own expected claims for the comparison. It never prices this path.
Everything else is priced to your own risk
Large group fully insured plans and experience rated MEWAs are both rated this way, and this gives employers more ability to shape benefits plan design than community rated fully insured. Claims made by your group move your renewal, and they are damped toward the manual rate by a credibility weight that takes group size into account. For example, single year claims from a group of 50 lives are only modestly credible but claims from a group of 6,000 lives are fully credible.
PEOs get handled separately. We assume a default renewal of about 13% a year (a Benefitra modeling assumption, not a published national average), with occasional much larger jumps. This is because a PEO reunderwrites your group. The default renewal is not state specific, because PEOs pool members nationwide. You can use your PEO's actual renewal instead if you want.
This is why an experience rated MEWA does not renew like a pooled trust such as Taft-Hartley. The Taft-Hartley trust acts something like a community pool. Everyone shares one renewal, drawn from a bounded distribution around a selected average renewal (about 3% a year in the 2026 edition, a Benefitra modeling assumption).
There are two distinct ways of self funding, Level Funded and Self Funded. They renew on different bases too. Level Funded is self funding inside a carrier package that includes stop loss insurance. It is medically underwritten at bind, and that is why a healthy small group can be offered a level funded rate below community rated fully insured. Level funding also has its own aggregate corridor (default ~120%) which is billed monthly, and therefore it is renewed on the package's own basis. Some employers work together with a major carrier on such bundled arrangements. Others prefer to keep more direct control through traditional self funding. Self Funded plans fund their own claims directly up to a per person stop loss deductible, plus fixed costs and stop loss premium. An aggregate attachment caps the worst year total, and they renew on their own basis rather than relying on the corridor associated with level funding. The Self Funded Captive adds a partially refundable layer of shared risk as well.
During good years, level funded, self funded and captive groups keep some of whatever money remains after they pay claims. Pooled plans and fully insured plans never return a surplus like that. For large group fully insured, PEO and MEWA structures, employers rely on administrators or carriers to manage the plan using the chosen model. For all of these, the incidence engine drives both the level and the volatility.
"Level Funded" and "Self Funded" are distinct arrangements that renew differently
Yes, both are ways to self fund but they remain different arrangements. The tool prices and renews them differently too. Employers that look for greater customization and vendor choice can find real advantages in traditional self funded arrangements.
Level Funded is self funding that comes entirely from within a carrier package and includes stop loss insurance along with a bundled TPA. Monthly payments are fixed in advance and part of the surplus is refunded in a good year. Also, it has its own aggregate corridor (default ~120%, billed monthly). Because this convenience is priced, it usually costs about 3 to 10% more than traditional self funding (a Benefitra estimate from quoting experience rather than a published figure).
Self Funded is traditional self funding. The group pays for claims directly and retains claims only up to the specific stop loss deductible, and the aggregate attachment caps the year. Pricing is done independently rather than based on the level funded corridor.
When quoting, we notice something. In Benefitra's quoting experience (this is not a published study), Self Funded typically quotes lowest at entry. Next comes the Self Funded Captive. Level Funded costs the most up front because the carrier packaged convenience costs a little more. Each option then renews based on its own terms. In practice, the level funded package is how smaller employers most often self fund. Thus the tool will show Level Funded as the default for groups of 100 or fewer lives and Self Funded above that. That's only a default, and you can switch and compare them side by side if you wish.
The insight the tool is built to surface
Community rated fully insured policies charge every small group the average cost of the pool. So a group with healthier people than average pays more than it should and subsidizes the pool, and it can often price below that premium by self funding or level funding to its own low risk. On the other hand, a group with people who are less healthy than average pays less than it should and benefits from being subsidized by the pool. For that sicker group, community rated fully insured works as a genuine hedge worth keeping while the group is eligible. In short, healthy groups tend to self fund and sicker groups tend to shelter in community rated fully insured. The tool tells you plainly which side of this line your group falls on. That is the single decision it exists to inform.
Which side you land on depends on the actual epidemiology of your group. That's why uploading a census is important (Section 4). Without a census, the tool estimates your position from age along with a health selector. When you provide one, it measures people member by member.
State law can override the recommendation. If self funding can’t legally be placed at your size, even a very healthy group gets pointed to what it can actually buy. An example is New York, where self funded, level funded and self funded captive plans need at least 101 full time equivalent employees. Groups with 100 or fewer are considered small group in New York and cannot use those types of plans. So their options are only fully insured, PEO, Taft-Hartley and MEWA, and the other paths are removed. D.C. has a similar rule as well.
4. Census, claims and other inputs
It needs to use your real numbers instead of a synthetic average. It’s critical that we get accurate inputs here because the simulator is built around your actual funding situation and not some general average. Default values are just plainly labeled fallbacks ("Modeled. Edit to make it yours") for the illustrative case where you leave everything blank. As you fill in more details, the anchor becomes sharper.
A better fit supports stronger financial decisions. Indirectly, it supports better employee health outcomes too.
What you can provide
| INPUT | WHAT IT DOES |
|---|---|
| Current premium and funding path | Anchors the cost level every path is measured against, in your own dollars. |
| A census. The age (and, where provided, gender) of each member | Sets each member's exact incidence rates in the catastrophe engine and pins down whether your group is healthier or sicker than the community pool. |
| Claims data. Known paid claims dollars, a loss ratio, or paid PMPM | The strongest anchor there is for the experience rated paths. The tool scales its modeled distribution so its average matches your actual claims, keeping the epidemiological shape while your dollars set the level. |
| Optional refinements. A stop loss quote (specific deductible and aggregate attachment), your last renewal percentage and the reason behind it, and an employer contribution level for employers comparing an ICHRA style alternative | Each sharpens the relevant path. |
Where the math runs, and what is sent. When you press run, the group level inputs you entered (state, size, ages as an average, premium, and optional claims totals) go securely to the pricing server of Benefitra. There the server runs the simulation and returns results. Census and claims files themselves are read inside your browser, and they are never uploaded.
What leaves the browser from a claims file. When you upload a claims file, only summaries are sent. This means your average monthly claims and your trend. For each large claimant we send just the condition category, the dollar amount and whether the claim is still ongoing. We never send names, birth dates, member IDs or any row of your file. If the file includes a column for names, we reject that file.
Numbers derived from defaults carry a visible "Modeled" tag. Numbers you type in are also clearly marked as yours. If there are missing pieces of information, the tool steps down gracefully. First it tries using your claims. If those are not available, it estimates using your premium and a labeled expected loss ratio. As a last resort, it uses a labeled community default. At every step it lets you know which one it used.
5. The cost containment overlay
We have an optional overlay for the self funded and captive paths that helps address avoidable high cost claims in self funded arrangements. It works by modeling clinical cost containment strategies, which are the levers a self funded employer can actually pull to bend the bad year spike down. By default this feature is turned off. If you turn it on you can explore how much thinner the catastrophic tail becomes and also see which conditions drive this tail. Real conditions generate the tail (Section 2), so each lever haircuts the realized condition mix of that scenario, and savings scale naturally because the reduction depends on which conditions actually show up. For a healthy group or a large group the reduction is small. But for a hot small group the reduction tends to be larger.
The strategies it models
| STRATEGY | WHAT IT TARGETS | EVIDENCE |
|---|---|---|
| Centers of Excellence (COE) | Major surgical episodes. Orthopedic / MSK, cardiac, transplant, some cancer surgery | Strong |
| Reference based pricing (whole plan) | Facility charges plan wide, benchmarked to a multiple of Medicare | Strong (price) |
| Direct cash pay | Routine and shoppable care bought at transparent cash prices, with a PPO backstop | Strong (price) |
| Specialty Rx management (conservative / aggressive) | Specialty & gene drugs, oncology drug slice, autoimmune biologics | Moderate |
| High cost / dialysis carve out | ESRD / dialysis and defined catastrophic conditions | Strong (dialysis) |
| Care navigation | Steerage, site of care, avoidable ER / readmissions / low value care | Moderate |
| Direct Primary Care (DPC) | Broad chronic / frequency reduction. Amplifies COE & navigation | Moderate |
The overlay names no vendors and focuses on operational strategy over vendor branded services. It models the mechanism directly, like "direct cash pay", instead of naming any particular cash pay network. This ensures that the estimate reflects strategy rather than a sales pitch.
Two levers behave differently from the other ones. Reference based pricing and direct cash pay reprice facility care plan wide. These do not trim just one type of claim, so we model them against healthcare spending broadly rather than focusing solely on the catastrophe tail. For the 2026 edition, whole plan reference based pricing usually trims roughly 15 to 30% of total plan cost. Direct cash pay with a PPO backstop trims roughly 20 to 45%. A whole plan RBP or cash pay model replaces the traditional PPO relationship, which means exclusivity rules apply. We also avoid stacking two standalone strategies that could not coexist in a single real plan design.
How the overlay is modeled
This feature does not make up savings. It works by reattributing and estimating, and it does this in four disciplined steps.
- Read the realized tail. In every simulated bad year the engine already knows which conditions actually fired and what they cost (cancer, cardiac, MSK, specialty Rx, NICU, dialysis, transplant, autoimmune, and the rest). There's no fixed share table. The mix is whatever that run drew.
- We stick strictly to what a lever can reach. Each strategy impacts just the addressable part of the conditions that it actually targets (like COE the surgical slice, specialty Rx management the drug slice, reference based pricing and direct cash pay the facility slice, and so forth). We are very careful indeed about what really is addressable.
- Use a sampled, ranged haircut. Instead of a fixed savings amount, the saving on that reachable slice comes from a distribution with min, mode and max values (PERT / triangular). This means the uncertainty flows into the output bands and you do not end up with false precision, which would be misleading.
- Stack on the residual. Strategies apply one by one to what's left after the lever before it, so overlapping levers don't double count. The total is bounded by each strategy's evidence based rate. It's also bounded by how much of that scenario's cost is genuinely containable, a share that comes out of the realized mix and is capped at 85%. We never assume routine and fixed costs away. In a healthy year it's a small slice. But in a bad year for a small group dominated by one catastrophic claim, it can be much larger, because that's genuinely how concentrated and containable those dollars are.
For a midage group with every applicable lever turned on, we see that model runs project a reduction in catastrophic tail dollars somewhere around 15 to 22%. This is a share of modeled catastrophic tail dollars, a different measure from the reference based pricing and cash pay figures above (those are shares of total plan cost). Strongest evidence comes from Centers of Excellence (RAND and peer reviewed bundled surgery studies) and from the reference based pricing / direct cash pay price gap (prices charged by facilities are well below commercial benchmarks). Care navigation and aggressive specialty Rx or high cost steering rely on softer evidence that is more based on vendor reporting. There are also caveats about patient access and legal concerns as well.
Read these as ranges. Ranges don't amount to promises. Savings from each lever are uncertain and depend on your vendors, your population, and how you actually implement the strategy. Some levers rely on softer or vendor reported evidence and have legal and access caveats. You can use the overlay to explore what containment could do to your tail. It is not a projection of what it will do. Modeled savings are ranges rather than guaranteed results.
6. Reading the results
A distribution of five year costs only helps if you can actually take action based on it. So this build wraps the engine with an interpretation layer. The goal is to make the trade off clear and not obscure it by hiding the uncertainty.
The percentiles you see
Each funding path gets its simulated costs reported at five percentiles. The 5th, 25th, 50th (median), 75th, and 95th. On the chart the median is the navy line. The 25th to 75th percentiles make the darker inner band, which is the middle half of outcomes. The lighter outer band runs from the 5th to the 95th percentile, a 90% planning range. Read the 5th percentile as a good luck year and the 95th as a bad luck / catastrophic year. The median is the honest "typical" outcome. Why do the main cost charts stop at the 5th and 95th percentiles? At these simulation run counts the extremes are too noisy to read as decision numbers. The one exception is the cost containment chart, which also shows the 99th percentile so you can see how containment acts on the most extreme simulated years. Take that edge as a rough indication, not a decision number.
Trend to renewal, not just a five year total
Along with showing five year totals, each funding path also shows a projected average annual renewal percentage. This helps you see the trajectories that separate the paths and not just where they land in year five. Why is this useful? For example, if one path starts cheap but renews at 12% a year, by year three its cost could surpass another path which starts off higher and renews at 6%. Viewing renewals like this highlights the difference clearly.
A plain language "why this wins"
Instead of getting just a bare ranking that you have to work backwards to understand, you get a risk adjusted recommendation. It includes a written explanation in plain English of why one particular path is favored for your group. Reasons include your health relative position, the size of your group and your tail exposure.
Conservative model and documented client results
The tool can present its comparison on one of two bases, and it labels which of the two is showing.
Conservative model (the default). Every alternative path has a price based on the data model we talked about earlier and is anchored to your own premium. That's the cautious read. It doesn't assume you will get top tier results, and that's the honest planning range you should treat as your basis.
Documented client results (optional). Flip a toggle and the alternatives get reframed with results from Benefitra placements plus one vendor statement.
PEO. For Benefitra clients who moved to a PEO, our case studies average about 37% savings versus their fully insured renewal (internal records, available to clients on request). The calculator plans with a more conservative 28% figure. Results vary by group. Some save less, some save nothing. Past results don't predict future results. And the PEO figure is applied only at 50 or fewer enrolled.
Captive. This one is a vendor statement from Roundstone, a captive provider. "Two thirds of our customers save enough in their first four years with us to pay the premiums for their entire fifth year. And 100% save money, full stop." (Roundstone, Aug. 18, 202110. Retrieved 2026-09-29 ET). It's the vendor's own claim. Benefitra hasn't verified it, and it isn't Benefitra client data.
So it shows what managed groups have reached. It doesn't promise yours will.
In both modes, any real quote or current path premium you enter takes priority over the modeled figure, every time. The mode just reframes the paths you have not priced with your own numbers. Use the conservative basis when making plans. The client results view is context, and it is clearly marked as such.
Benchmark cost context
Are you starting high, low, or typical? To tell you, the tool sets your current cost per member against public benchmarks. Our reference point is the KFF Employer Health Benefits Survey 20251. There the national average single coverage premium was about $9,325/year. Small firms (KFF defines these as 10 to 199 workers) came in near $9,211 and large firms near $9,361. Seeing your PMPM against those bands frames the whole comparison before you weigh funding paths.
Onboarding, PDF report and broker version
Guided onboarding. A quick walkthrough on the first run helps you understand the inputs and what the output bands mean. That way, when you get your very first result, it won’t just be a wall of numbers.
PDF report export. You can export a shareable PDF report of your run (email gated) and bring it to your broker, CFO, or advisor.
Broker version. Advisors have their own separate, access gated build that lets them edit calibration per condition. Brokers can tune incidence and cost assumptions to a specific book they handle. This is kept private and separate from our main public tool, and we never quietly change the default calibration you see here.
7. Validation and backtest
We should only trust a model based on what the model has actually done. Validation is a critical part of any methodology for decisions about healthcare funding. We prefer presenting you with an honest and partial record versus one that is polished and overstated. Here is exactly where validation stands right now.
Backtest of the fully insured renewal default
We backtested on CMS small group rate filings from each state (plan years 2014 to 2026, 50 states) and also on AHRQ MEPS-IC employer premiums (1996 to 2025), retrieved Sept 27, 2026. This is a look back test. For each past year we used only the data available at that time and forecast one, three and five years ahead. We then scored these forecasts against what actually happened. The comparison was a recent weighted trend (an exponentially weighted moving average, EWMA, with α = 0.5) against the trailing six year average.
| HORIZON | CMS STATE SMALL GROUP FILINGS. ERROR, EWMA VS SIX YEAR AVERAGE | MEPS-IC SMALL FIRMS (<50). EWMA MINUS SIX YEAR AVERAGE | READING |
|---|---|---|---|
| 1 year | 4.17 vs 4.35 pp (300 state years, 6 origin years. Difference not significant) | Full sample. EWMA slightly better (-0.08 single, -0.20 family). Since 2010. Six year average slightly better (+0.14, +0.30) | About tied |
| 3 years | 3.21 vs 2.87 pp (six year average better in 4 of 4 origin years) | Since 2010. Six year average better (+0.41 single, +0.79 family) | Six year average better |
| 5 years | 2.89 vs 2.38 pp (only 2 origin years. A longer check with 5 origin years gives +0.45) | Since 2010. Six year average better (+0.38 single, +0.90 family). Full sample. No significant difference | Six year average better |
Here the error is root mean square error in percentage points of annual rate change, and lower is better. The MEPS-IC columns show the difference in error (EWMA minus six year average), so a positive number means the six year average did better. Source. Benefitra renewal horizon backtest, Sept 27, 2026 ET.
What it shows. For next year's renewal, the EWMA and the six year average come out about tied. At three to five years, the six year average beats the EWMA in both datasets (in MEPS-IC, this is in the period since 2010). The 2026 edition uses the six year average for every year, which the backtest's point estimates favor for years 3 to 5. For year 1, the recent weighted trend did about as well.
We have medium confidence. Both datasets are consistent. But we don't have many independent origin years and the five year CMS result depends on just two of them. Every forecasting method that we tested under forecast renewals from 2020 to 2026 (by about 1.3 points on average in year one, on the CMS state panel for forecast origins 2020 to 2025). So please read the projections with an upside weighted range.
From 2020 on, the CMS figures are requested rates, meaning the rates insurers filed, and not approved rates. The public files have no approved field after 2019. They are filed averages and not the renewal that a specific group receives. MEPS-IC is a survey with sampling error, and it mixes insured and self funded plans. The backtest tests the renewal default only, and not the funding recommendation. An earlier size band test that was built on KFF survey series has been withdrawn. It will not return until it is rebuilt on public domain data with published files.
Underwriter review
Borka Skoric, an underwriter at Blackwell, looked at this. Blackwell Captive Solutions is a captive program that Benefitra works with and may recommend (see Section 9). The review considered how the funding arrangements renew relative to each other. This is not an actuarial certification of every calculation. We document our methodology so it can be put in front of an independent actuary. An independent actuarial review is still a stated goal (see below). We do not claim we have completed this yet.
The Renewal Index and the path to peer review
In the 2026 edition, the community rated renewal default is calculated as your state's six year average of filed small group renewals. This same filing history serves as the basis for the Benefitra Renewal Index, which is transparent and versioned and not a black box forecast. We designed this index because we want people to see the basis for the community rated branch. This index uses state filed small group renewal trends, decomposed and updated over time. The 2027 edition also shows a planning horizon view of that index (see the 2027 methodology). It is an estimate based on public filings and not a forecast of any specific group's renewal.
Beyond the renewal backtest above, the credibility roadmap follows an intentional order. We start with an independent actuarial review of the methodology. When per employer data (state DOI filings, real claims) becomes available, we then do a firmer segmented hit rate. Future reviews also need to take into account changing regulations as additional data sources come on line. Only after this do we do a peer reviewed write up. Misses get published along with hits at each step. A funding tool that hides its failures is the one you should distrust.
The backtest is a fast workstream and runs on an ongoing basis. Independent actuarial certification and a peer reviewed publication happen separately at a slower pace, and we will link them here once they land. We won’t publish an accuracy figure for the recommendation until published data supports it.
8. Limitations
This section is right up front on purpose. Here honesty is what credibility rests on. Deciding on funding is a health and money (YMYL) decision. The tool is just one input that goes into making this decision. It's not the answer.
- This is decision support, not advice. Using this tool won’t create an advisor client relationship. It isn't an insurance quote either, and it doesn’t recommend a specific product for your specific circumstances. Every number here should be treated as a modeled estimate to discuss with a licensed professional.
- It gives honest ranges rather than forecasts. Each output shows a distribution of possible outcomes. What really happens can’t be known with certainty. But this tool can show a range of plausible futures through running many simulations.
- It can't predict individual claims, and one very large claim no one can foresee can push you well outside even the modeled bad year band. We model the tail statistically from population incidence rather than by being clairvoyant.
- Its default assumptions may not fit your specific group. Incidence rates, condition mix, cost distributions and renewal behavior have all been calibrated to population level research and typical groups. An unusual demographic, industry, geography, claims history, internal departments or workforce pattern can make the defaults a poor fit. That is why this tool allows you to replace defaults with your own census and claims.
- Numbers are modeled estimates and not adjudicated dollar amounts. Costs are commercial billed figures that are then reduced by a network discount factor and thinned by severity gates. Rules like recurrence and persistence are the softest inputs. They are not settled facts and can be adjusted.
- The condition engine shapes the tail, not the headline. By design, the average catastrophe cost is pinned to your expected budget. Detail for each condition refines the shape of the bad year tail and the healthy vs sick read, but it doesn't make the estimate of a typical year more precise. We made that trade off intentionally, and it means the value of the detailed engine lies in the risk picture and the recommendation rather than in the central estimate itself.
- Your files stay in your browser. Summary information is sent to our server. Census and claim files are read directly on your device and are not uploaded, and name columns are rejected automatically. The simulation itself runs on Benefitra's pricing server. This server receives your group level inputs and the claims summaries from Section 4. Checks in your browser cannot police everything, so please keep identifying information out of your file. Handle the file on your own computer as your responsibility.
- This tool doesn't replace a licensed advisor or an actuary either. Making real decisions about funding involves things like underwriting, getting real stop loss insurance quotes and reviewing plan documents. Professionals also bring judgment, which this tool lacks.
- Cost containment estimates are modeled ranges that depend on vendor performance and implementation. Some of them rest on softer evidence while several have legal and patient access caveats. Think of them as a look at possible savings, but they don't promise any savings.
- Data lags and has gaps. Public sources come out periodically and lag the market, and state rules change too. Figures reflect the most recent public data available as of the last updated date rather than showing real time conditions.
- This backtest is limited. It only covers the fully insured renewal default. It uses filed state averages (requested rates from 2020 on). The test relies on just a few independent years at the five year horizon. Every method it tested under forecast 2020 to 2026. And importantly, this isn't a per employer accuracy rate.
- Structures have risks that we don't model. For pooled arrangements (MEWA / Taft-Hartley), the modeled range holds only as long as the arrangement stays financially healthy. But this tool itself can't look directly at a specific trust's solvency, operations, or financial health.
Bottom line. Use the simulator to frame the conversation and get a feel for the shape of the trade off. Before you decide, get a real quote and a licensed advisor. Does a number here ever seem too good to be true for your situation? It probably is. Ask us to walk you through the assumptions.
9. Disclosures
Benefitra is a licensed insurance brokerage. We may earn commissions or fees when clients buy coverage, and that includes Taft-Hartley, PEO and captive arrangements that this calculator can recommend. Benefitra funded this research. Blackwell Captive Solutions is a captive program Benefitra works with and might recommend. Results are statistical estimates, not quotes, promises, or actuarial opinions. AI tools assisted with analysis and drafting (Grok by xAI for research and drafting. Claude by Anthropic for quality control and editing). Before publication, Sam Newland, CFP®, checked all figures.
10. Frequently asked questions
Is this an insurance quote?
This is not an insurance quote. Results from this simulator are modeled estimates rather than quotes, and using it doesn't create an advisor client relationship. Real funding decisions need underwriting and actual stop loss insurance quotes along with a review of plan documents. Regarding Benefitra, it is a licensed brokerage that can earn commissions on some of the options displayed. So treat all numbers as starting points to discuss with a licensed advisor before you sign anything.
Why does it show a range instead of one number?
Because one number alone hides the risk involved. The engine runs your group's next five years thousands of times (by default 5,000 runs for groups of 50 or fewer enrolled employees and 2,000 for larger groups). Then it reports the 5th, 25th, median, 75th and 95th percentiles from all those simulation runs. The spread is what really matters, because the bad claims years are what separate one funding path from another.
Why does the tool say my group should stay fully insured or self fund?
The main thing to consider is which side of the community pool your group falls on. Small group fully insured premiums charge every group the pool's average. Groups that are healthier than average end up paying too much and can often price below that premium by level funding or self funding. On the other hand, if a group is sicker, the pool helps them out. That means community rated fully insured is still a hedge worth keeping. Size of the group and state law also affect which option the tool picks.
Do I have to upload my census or claims? Where does that data go?
Uploading your census or claims is optional. If you don't upload a census, the tool estimates your position from age and a health selector. When you do upload one, it measures it member by member. Census and claims files are read in your browser and are never uploaded. The only information that goes to Benefitra's pricing server is group level inputs and claims summaries. No names, birth dates or member IDs ever go there. Files that contain a column for names are just rejected outright.
How accurate is it?
So far only the fully insured renewal default has been tested. We've backtested it using CMS small group filings (2014 to 2026) and MEPS-IC premiums (1996 to 2025). The six year average came out about tied with a recent weighted trend for year one, and it did better at three to five years. Confidence is medium. Every method tested under forecast 2020 to 2026, and we won't publish an accuracy figure for the recommendation until published data backs it up.
Does the cost containment overlay promise those savings?
The cost containment overlay does not promise those savings. This overlay explores what clinical cost containment could do to the bad year tail on the self funded and captive paths. Savings from each lever come from a range. They depend on your vendors, your population and how the strategy is carried out. Some levers rely on softer or vendor reported evidence, and there are legal and access caveats. So treat the output as an exploration of potential.
Why isn't self funding an option for my group?
Typically it's state law. If a state's statutes restrict small group stop loss coverage, the self funded paths are removed. They just don't show up as if you could buy them. In New York, self funded, level funded and self funded captive arrangements need at least 101 full time equivalent employees, and D.C. has a similar rule. The self funded captive is also withheld for the very smallest groups that fall below the program's enrollment floor.
Should I make my funding decision based on this tool?
Use this to frame the decision, but do not make the decision with it. This simulator displays the shape of the trade off between predictable premiums and exposure to claim volatility. After viewing this, get a real quote and a licensed advisor before you decide. If a number looks too good to be true for your situation, ask us to walk you through the assumptions.
12. Version, citation and corrections
Version. 2026 edition, v2.1.2 (engine calibration cal-cdf51912d2cd). First published September 14, 2026 ET. Updated September 29, 2026 ET.
How to cite
Newland, S. (2026). 2026 Health Plan Funding Simulator Methodology (2026 edition, v2.1.2). Benefitra. Updated September 29, 2026. https://benefitra.com/health-plan-funding-simulator-methodology/
License
© 2026 Benefitra. Text and Benefitra derived tables are licensed under CC BY 4.0 (https://creativecommons.org/licenses/by/4.0/). You may share and adapt with credit to Benefitra and a link to this page. Third party data (CMS, AHRQ, KFF, vendor figures) remains under its owners' terms. The Funding Simulator software is proprietary and not licensed for reuse.
Corrections
Found an error? Email info@benefitra.com. Every correction is logged below with the date, what changed and which numbers moved.
Changelog and errata
| VERSION AND DATE (ET) | WHAT CHANGED |
|---|---|
| v2.1.2, Sept 29, 2026 | Underwriter named with consent. NY rule corrected to 101+ FTEs. PEO case study average reconciled. Captive 18% removed, 2026-09-29. Added the Blackwell Captive Solutions disclosure. Replaced the year 2 glide recommendation with the planned calculator update backtested Sept 29, 2026, and restated the under forecast bias from that backtest. No calculator numbers changed. |
| v2.1.1, Sept 29, 2026 | Placeholders resolved per Sam, 2026-09-29. Named the AI tools (Grok by xAI, Claude by Anthropic) and the fact checker (Sam Newland, CFP®). Confirmed the byline and corrections contact. Stated the basis of the PEO 28% client savings figure. Added the license (CC BY 4.0 for text and Benefitra derived tables. The simulator software is proprietary). No calculator numbers changed. |
| v2.1, Sept 29, 2026 | Corrections from Benefitra's QC review (Sept 26 to 27, 2026). Replaced the KFF based size band backtest and its "Supported" verdicts with a CMS and MEPS-IC renewal backtest. Removed "validated" wording and the named reviewer (pending consent). Added the disclosures box. Restated client results (PEO above 28%, captive 18% as a vendor figure) and removed the undefined "self funded about 1% under the captive". Listed all 17 named conditions. Labeled the PEO 13% and Taft-Hartley 3% defaults as Benefitra modeling assumptions. Stated the New York rule and the 2021 to 2026 window. Removed "error bars" (none are shown). Added the KFF firm size definition. Added the CFP® mark, version, dates, summary, citation and this log. No calculator numbers changed. |
| v2.0, Sept 25, 2026 | 16 corrections from the Sept 25 methodology audit. (1) pricing runs on Benefitra's server, not only in the browser. (2) listed the claim summaries that are sent. (3) run counts corrected to 5,000 / 2,000, range 500 to 10,000. (4) removed tornado chart and what if sliders. (5) removed tobacco share and family tier inputs. (6) Taft-Hartley 2026 renewal restated at about 3%. (7) added New York / Vermont no age rating and the 1 to 50 / 1 to 100 small group cutoffs. (8) fully insured renewal default corrected to the state six year filed average. (9) calculator link corrected to /funding-simulator-2026/. (10) updated date corrected. (11) reference based pricing (15 to 30%) and cash pay (20 to 45%) stated separately. (12) "no savings ceiling" corrected to the 85% cap. (13) 99th percentile shown on the containment chart only. (14) removed unsupported filler figures. (15) softened the claim concentration statement and tied it to its source. (16) PEO given its own rating row. |
| v1.0, Sept 14, 2026 | First publication. |
More on Health insurance funding
Related funding arrangement
- Funding arrangements compared Fully-insured, level-funded, self-funded, captive, ICHRA, PEO and Taft-Hartley plans side by side.